

Diabetic Neuropathy: What You Need To Know





Last updated on 22 Aug 2026
Among the problems linked to diabetes, the one which is always the hardest to cope with is diabetic neuropathy. This is because it develops slowly, the signs can be easily overlooked, and it can affect different systems in the body.
Do you feel the tingling sensation in your feet? You are not overreacting too much. What about the feeling of burning? Did you experience any dizziness upon standing up, the slow emptying of the stomach, or sudden sweating?
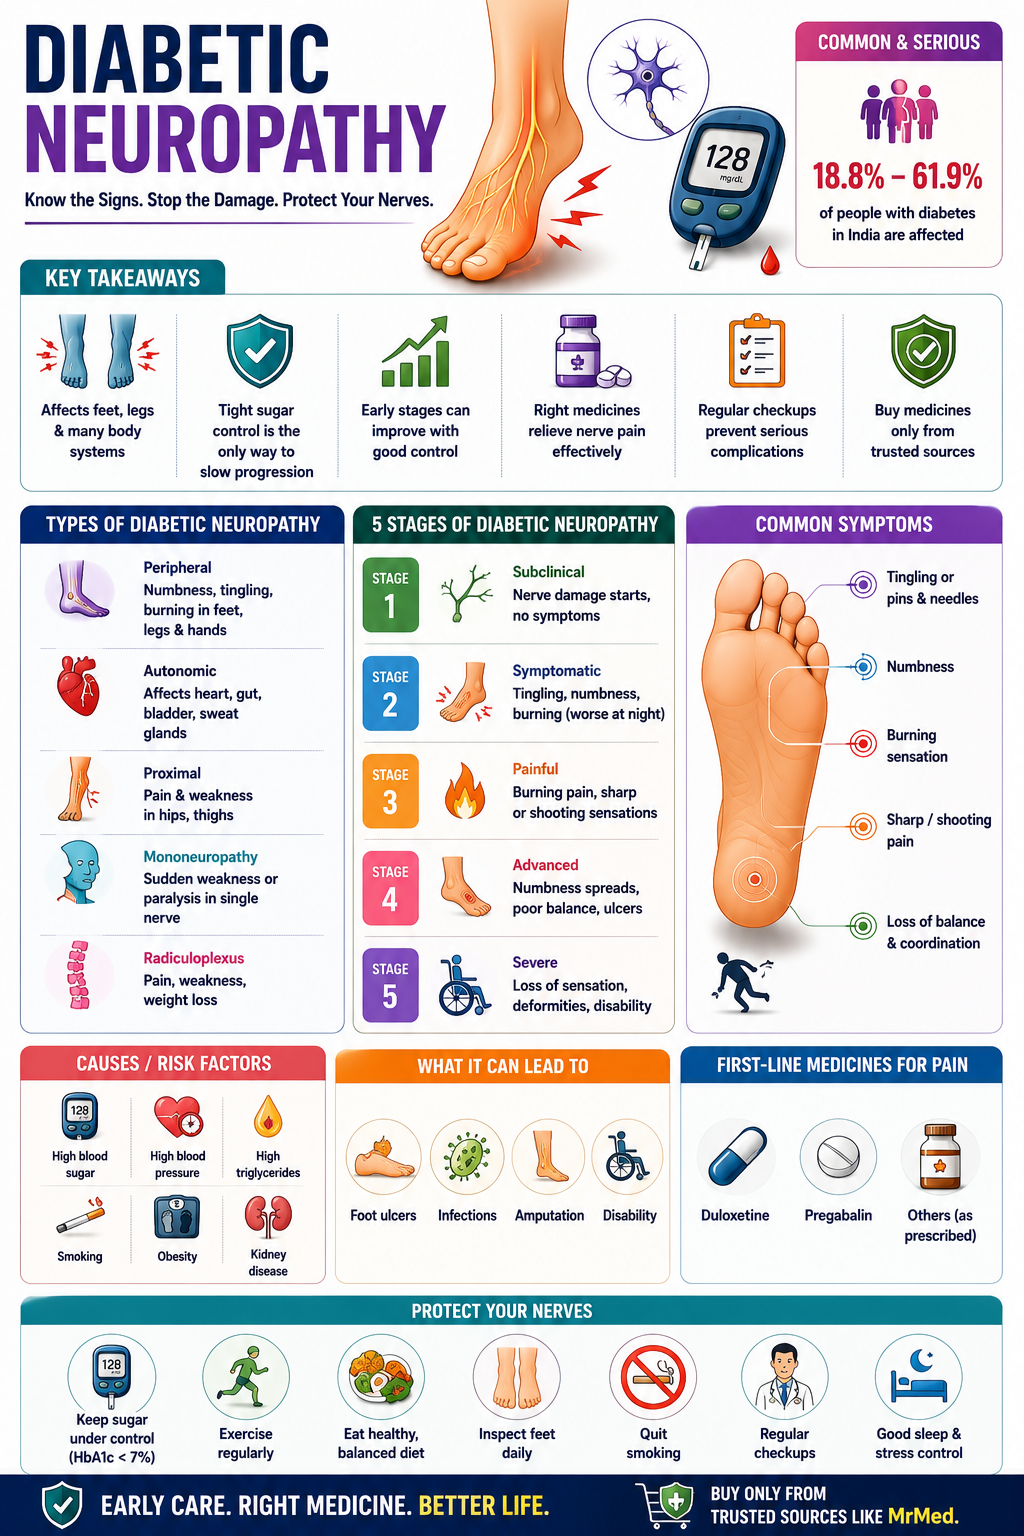
Key Takeaways
|
What Is Diabetic Neuropathy?
Diabetic neuropathy is defined as neural damage caused by prolonged exposure to high levels of blood sugar. All nerves in the body can be affected, but to begin with, only those that supply the longest nerve trunks, such as the ones going to the feet and legs, are affected to a significant degree. This length dependency explains the typical distribution of symptoms associated with diabetic neuropathy.
The mechanisms behind diabetic neuropathy include an accumulation of advanced glycation end-products (AGEs) in nerve tissues, oxidative stress that impairs mitochondrial function in nerve cells, reduced blood supply to the nerves due to microvascular damage, and inflammation. These processes result in slow nerve conduction velocity, damage to the myelin sheath insulating the nerve fibers, and subsequent degeneration of the nerve fibers.
Causes of diabetic neuropathy can therefore be summarised as follows: chronic hyperglycemia, diabetes duration, poor glycemic control, high blood pressure, high triglyceride levels, smoking, obesity, and kidney disease. The longer the blood sugar levels remain uncontrolled, the more damage the nerves sustain.
Dr Vijay Viswanathan, Head and Chief Diabetologist at MV Hospital for Diabetes, Chennai, first Asian President of D-Foot International, and co-author of over 250 peer-reviewed publications on diabetic foot and neuropathy, has confirmed the Indian burden plainly: "Diabetic peripheral neuropathy is particularly prevalent in India, affecting anywhere from 18.8 to 61.9 per cent of individuals with diabetes mellitus. Early detection is crucial for reducing associated complications."
Types of Diabetic Neuropathy
Diabetic neuropathy is not a single condition. It describes several distinct patterns of nerve damage:
Type | Nerves Affected | Main Features |
Diabetic peripheral neuropathy | Long peripheral nerves in the feet, legs, and hands | Numbness, tingling, burning, pain |
Diabetic autonomic neuropathy | Autonomic nervous system: heart, gut, bladder, sweat glands | Heart rate abnormalities, gastroparesis, bladder dysfunction, orthostatic hypotension |
Proximal neuropathy | Hip, thigh, buttock nerves (femoral nerve) | Sudden severe pain in thigh; muscle weakness; rare |
Mononeuropathy | Single nerve, often cranial or peripheral | Sudden wrist drop, foot drop, or cranial nerve palsy; usually self-limiting |
Radiculoplexus neuropathy | Nerve roots and plexus | Pain, weakness, weight loss often in older adults |
Diabetic Neuropathy Stages: How It Progresses

Understanding diabetic neuropathy stages helps identify the condition earlier and frame the urgency of glycaemic management:
Stage 1: Subclinical neuropathy: Nerve conduction velocity is already slowing; no symptoms yet. Only detectable on nerve conduction studies.
Stage 2: Symptomatic neuropathy: Tingling, numbness, or burning in toes and feet. Symptoms may be worse at night.
Stage 3: Painful neuropathy: More intense pain: burning, shooting, electric. Allodynia (pain from normally non-painful stimuli, such as bed sheets touching the feet). Significant impact on sleep and quality of life.
Stage 4: Loss of sensation: Paradoxically, pain may reduce as more nerve fibres are lost. The feet go numb the most dangerous stage for unrecognised injury.
Stage 5: Severe complications: Foot ulcers, Charcot arthropathy (bone and joint destruction from repeated unrecognised trauma), risk of amputation.
Most complications occur at Stage 4 and 5 when patients feel less pain and therefore notice problems less.
The most recent Indian hospital data reinforces this. A 2024–25 cross-sectional study at a tertiary care hospital in Tamil Nadu, covering 310 Type 2 diabetes patients, found DPN prevalence of 39.3 per cent with longer diabetes duration, poor medication adherence, and uncontrolled HbA1c as the strongest independent predictors.
What Are the Symptoms of Nerve Damage Caused by Diabetes?
What are the symptoms of nerve damage caused by diabetes? The five main symptoms of diabetic neuropathy in its peripheral form are:
Tingling or pins and needles: typically starting in the toes
Numbness: reduced ability to feel heat, cold, or touch in the feet
Burning pain: often worse at night, affecting sleep significantly
Sharp or shooting pain: electric-like jolts, particularly in the feet and lower legs
Weakness: particularly in the feet and ankles; foot drop in advanced cases
Diabetic foot symptoms that specifically warrant urgent medical attention include:
Any wound, blister, or break in the skin on the foot that the patient did not feel
Swelling, redness, or warmth in one foot (possible Charcot arthropathy)
Colour changes, pale, blue, or black discolouration
Pus or discharge from any skin breach
Diabetic autonomic neuropathy symptoms are different and often overlooked:
Postural hypotension (dizziness when standing up)
Resting heart rate above 100 bpm (cardiac autonomic neuropathy)
Feeling full after very small meals; nausea; vomiting (gastroparesis)
Erectile dysfunction or vaginal dryness
Bladder problems: urgency, incontinence, or incomplete emptying
Excessive sweating in the upper body; loss of sweating in the lower body
Diabetic Neuropathy Diagnosis: What to Expect
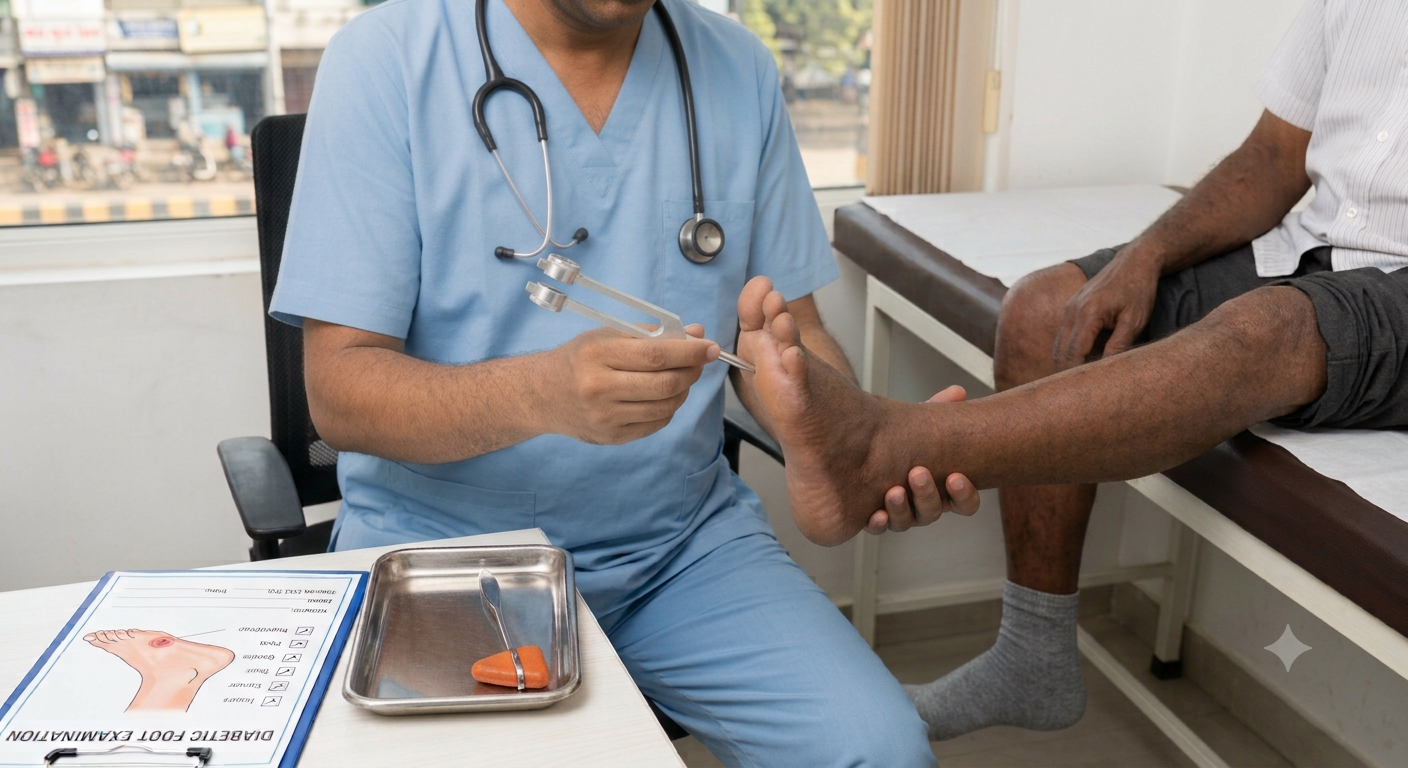
Diagnosis involves a combination of clinical assessment and, where needed, objective nerve function testing:
Monofilament test: A 10g Semmes-Weinstein monofilament is pressed against defined points on the foot. Inability to feel it indicates significant sensory loss. Every person with diabetes should have this test annually.
Tuning fork test: Tests vibration perception at the big toe and ankle.
Pinprick sensation: Simple clinical test for pain fibre integrity.
Ankle reflexes: Loss of ankle jerk is an early sign of peripheral neuropathy.
Nerve conduction studies (NCS): Objective measurement of nerve conduction velocity; used when clinical diagnosis is uncertain.
Autonomic testing: Heart rate variability, tilt table tests, and gastric emptying studies for suspected autonomic neuropathy.
The diabetic neuropathy StatPearls resource from the National Library of Medicine confirms that annual screening with monofilament and tuning fork (or biothesiometer) is the minimum standard for every diabetes clinic.
A 2025 biothesiometry screening study at a rural Indian tertiary centre found that 57.40 per cent of DPN patients had no symptoms at all and 27.49 per cent had feet at significantly elevated ulceration risk without knowing it. The Stage 4 phenomenon where nerve death eliminates pain is why diabetic neuropathy cannot be managed based on symptoms alone.
Diabetic Neuropathy Treatment: What the Evidence Supports
How to treat diabetic neuropathy? Treatment has two distinct goals: slowing progression and managing pain.
Treating the Underlying Cause
Tight glycaemic control HbA1c below 7 per cent, sustained consistently over years, is the only treatment that genuinely slows progression. The DCCT (Type 1 diabetes) and UKPDS (Type 2) trials both demonstrated that intensive blood sugar control significantly reduces neuropathy risk and progression. This is why diabetic neuropathy treatment always begins with optimising blood glucose, blood pressure, and lipids, not just reaching for a painkiller.
Diabetic Neuropathy Medication for Pain
First-Line for Pain? | Drug | Notes |
✅ Yes (ADA 2025 first-line) | Duloxetine (Cymbalta) | SNRI; 60 mg daily; most studied for DN pain |
✅ Yes (ADA 2025 first-line) | Pregabalin / Gabapentin | Alpha-2-delta ligand; dose titrated for effect |
Second-line | Amitriptyline | Tricyclic antidepressant; low-dose; useful for sleep-disrupting pain |
Third-line | Tramadol | Opioid; use cautiously due to dependence risk |
Adjunct for localised pain | Capsaicin cream | Topical; depletes substance P in peripheral nerves |
❌ Not recommended | NSAIDs / standard painkillers | Largely ineffective for nerve pain; risk of kidney damage in diabetes |
Diabetic Neuropathy Treatment at Home
Diabetic neuropathy treatment at home focuses on foot care and lifestyle modification:
Daily foot inspection: Check every inch of both feet every day; use a mirror for the sole. Look for any cuts, blisters, or colour changes.
Protective footwear: Never walk barefoot, even indoors. Use properly fitting, padded shoes at all times.
Warm water precaution: Test water temperature with your elbow or a thermometer before a foot bath; insensate feet cannot detect scalding.
Regular gentle exercise: Walking improves nerve blood supply and glucose metabolism. Physiotherapy-guided exercise programmes show measurable improvements in nerve function over time.
Smoking cessation: Smoking reduces nerve blood supply and accelerates neuropathy progression independently of blood glucose.
Best Supplements for Diabetic Neuropathy
Best supplements for diabetic neuropathy with some clinical evidence:
Alpha-lipoic acid (ALA): The most studied supplement for diabetic neuropathy; antioxidant properties shown to reduce neuropathic pain scores in European trials; 600 mg daily IV or oral.
Methylcobalamin (active Vitamin B12): Supports nerve myelin repair; commonly prescribed in India alongside standard neuropathy management.
Benfotiamine (fat-soluble B1): Inhibits advanced glycation end-product formation; some evidence suggests it may slow progression.
Vitamin D: Deficiency is common in diabetic patients and has been associated with worsening neuropathy; optimising levels is a low-risk, widely recommended step.
Always discuss supplements with your doctor some interact with diabetes medications.
Diabetic Neuropathy Home Remedies
For mild symptom relief, evidence-supported diabetic neuropathy home remedies include:
Warm foot soaks (temperature-checked) to improve local circulation
Elevating legs when resting to reduce swelling
Transcutaneous electrical nerve stimulation (TENS) available as home units; some evidence for pain relief
Capsaicin-based topical creams over-the-counter; burn sensation initially but desensitises nerve endings over weeks
Will Diabetic Neuropathy Go Away?
Will diabetic neuropathy go away? This is the most important question, and the answer is nuanced.
Yes, if caught early and blood sugar is controlled. In the subclinical and early symptomatic stages (Stages 1–2), sustained improvement in HbA1c can partially reverse nerve damage and prevent progression. Some patients who achieve tight control early report significant reduction in symptoms over months to years.
No, if significant damage is already established. Nerve fibres that have been lost do not regenerate in the same way. The goal at Stages 3–5 becomes pain management, functional preservation, and prevention of further damage and foot complications, not reversal.
Diabetic neuropathy reversal is therefore a realistic goal only for patients who act early. This is why diagnosis and glycaemic optimisation in the first decade of diabetes has such a profound impact on lifetime neuropathy outcomes.
FAQs
Q1. What are the 5 main symptoms of diabetic neuropathy?
Tingling, numbness, burning pain (especially at night), sharp or shooting pain, and weakness, typically starting in the toes and feet and spreading upward.
Q2. What is the best treatment for diabetic neuropathy in feet?
Tight blood sugar control is the most important intervention. For pain, duloxetine or pregabalin are first-line. Daily foot inspection, protective footwear, and prompt attention to any wound are non-negotiable.
Q3. Will diabetic neuropathy go away?
In early stages, yes, with sustained glycaemic improvement. Established nerve damage is not fully reversible, but further progression can be slowed, and symptoms can be managed effectively.
Q4. How to treat diabetic neuropathy at home?
Daily foot inspection, temperature-checked warm foot soaks, protective footwear, regular gentle exercise, smoking cessation, and blood glucose monitoring. Alpha-lipoic acid and methylcobalamin supplements may support nerve function; discuss with your doctor.
Q5. What are diabetic autonomic neuropathy symptoms?
Dizziness when standing, rapid resting heart rate, bloating and nausea after small meals (gastroparesis), bladder issues, excessive sweating in the upper body, and sexual dysfunction. These affect different systems than peripheral neuropathy but are equally important to identify.
Final Thoughts
Diabetic peripheral neuropathy is not inevitable. It is not untreatable. And it is not something to manage alone. But it requires consistent attention to blood sugar control above everything, to regular foot checks, and to not dismissing early symptoms as "just tiredness" or "just getting older."
If you have diabetes and you notice persistent tingling, numbness, or burning in your feet or any unexplained cardiovascular, digestive, or urinary symptoms, raise it with your doctor at your next appointment. Do not wait for it to worsen.
Early diagnosis, tight control, and appropriate management give the best possible chance of limiting the damage that diabetic nerve pain can cause over a lifetime.
Read Also
How Diabetes Medications Support Blood Sugar Control Beyond Diet
Type 1, Type 2, and Other Diabetes Types: What Makes Them Different
References
Savelieff MG, Elafros MA, Viswanathan V, Jensen TS, Bennett DL, Feldman EL. The global and regional burden of diabetic peripheral neuropathy. Nat Rev Neurol [Internet]. 2025 Jan [cited 2026 Jul 09];21(1):17–31. Available from: https://pubmed.ncbi.nlm.nih.gov/39639140/
Gowtham S, Anantha Eashwar VM, Thozhanenjan I, Nikhil CM, Narayanan K. Prevalence of diabetic peripheral neuropathy and its associated risk factors among patients with type 2 diabetes mellitus in the Chengalpattu District of Tamil Nadu. Cureus [Internet]. 2025 May 06 [cited 2026 Jul 09]. Available from: https://pmc.ncbi.nlm.nih.gov/articles/PMC12141643/
American Diabetes Association Professional Practice Committee. Standards of care in diabetes 2025. Diabetes Care [Internet]. 2025 Jan [cited 2026 Jul 09];48(Suppl 1). Available from: https://diabetesjournals.org/care/issue/48/Supplement_1
Disclaimer: This article is for general informational and awareness purposes only. It does not constitute medical advice. If you have diabetes and are experiencing symptoms of neuropathy, please consult a qualified physician, diabetologist, or neurologist for appropriate assessment and management.













Comments