


Psoriasis and Skin Cancer: Risk, Connection, PUVA Link & What Patients Should Know





Last updated on 28 Aug 2026
Psoriasis affects approximately 2 to 3 percent of the Indian population, translating to roughly 2.8 million people living with this chronic inflammatory skin condition. While psoriasis itself does not directly cause skin cancer, the various treatments used to manage psoriasis, particularly PUVA therapy, biologic medications, and immunosuppressive drugs, carry documented risks of increasing skin cancer development.
Understanding this complex relationship between psoriasis, its treatments, and skin cancer is essential for patients and healthcare providers to make informed decisions about therapy and implement appropriate surveillance strategies.
This comprehensive guide addresses the critical question: Does psoriasis cause skin cancer? It explores the mechanisms linking psoriasis treatments to skin cancer risk and provides practical guidance on monitoring, surveillance, and early detection for Indian patients with psoriasis.
Key Takeaways
|
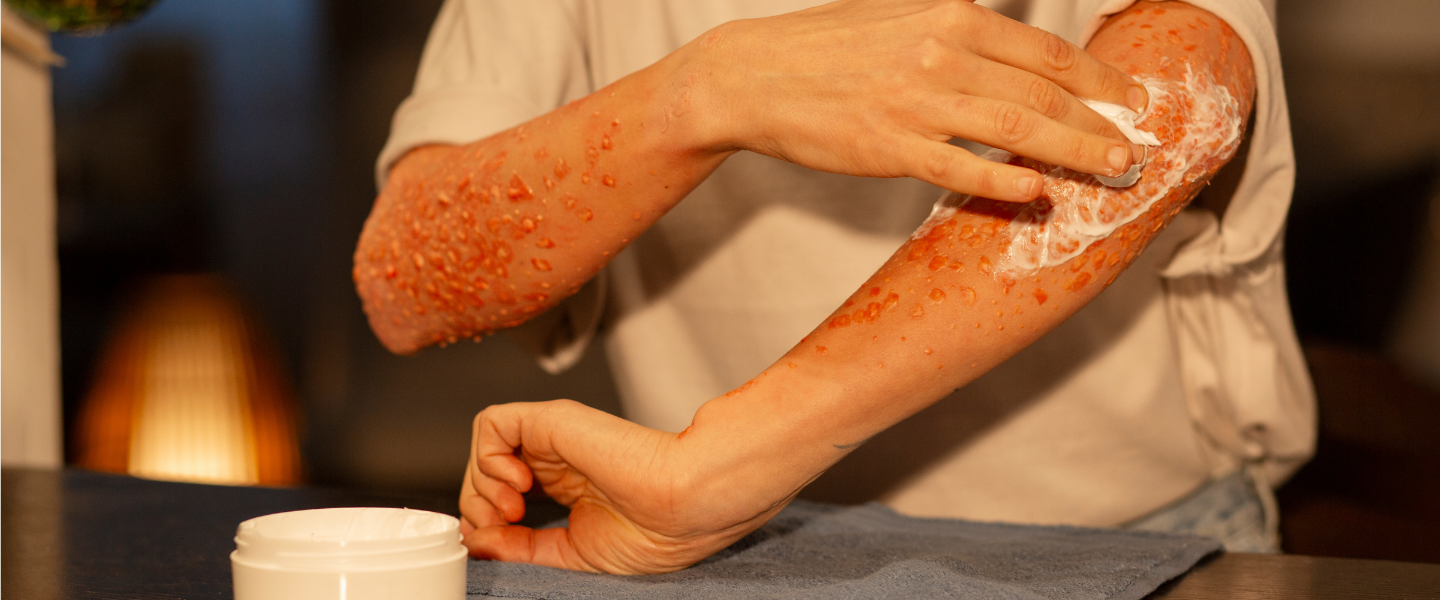
The PUVA Therapy Connection: How UV Treatment Raises SCC Risk
According to the British Association of Dermatologists, PUVA therapy increases SCC risk by up to 5 times in patients receiving prolonged treatment.
PUVA therapy, which stands for Psoralen plus UVA radiation, was historically one of the most effective treatments for moderate-to-severe psoriasis in India. The treatment involves taking oral psoralens followed by controlled UVA light exposure.
Key Points on PUVA and Skin Cancer Risk:
Decades of long-term follow-up data reveal a dose-dependent relationship between cumulative PUVA exposure and the risk of squamous cell carcinoma (SCC).
Risk is cumulative and dose-dependent; the more PUVA sessions a patient receives, the higher the cancer risk.
For every 100 sessions of PUVA therapy, there is an estimated 10 percent increase in cumulative SCC risk.
The British Association of Dermatologists recommends limiting lifetime PUVA exposure to fewer than 200 sessions to minimise the risk of skin cancer.
In India, PUVA therapy has been widely used and remains relatively affordable compared to newer biologic therapies.
Many Indian patients have received hundreds of sessions without skin cancer awareness of the cumulative cancer risk.
Biologic Therapies and Skin Cancer Risk: What the Evidence Says
Research published in JAMA Dermatology in 2016 demonstrated that psoriasis patients on biologic therapy had a 1.5- to 2-fold increased NMSC risk compared to untreated psoriasis patients.
Biologic therapies, including adalimumab, secukinumab, infliximab, and etanercept, have revolutionised psoriasis treatment by precisely targeting inflammatory pathways.
Clinical Evidence on Biologic Therapy and Cancer Risk:
Clinical trials and post-market surveillance have documented a small but measurable increase in non-melanoma skin cancer (NMSC) risk with biologic therapy use.
This remains substantially lower than the risk from PUVA therapy.
The mechanism is thought to involve inhibition of inflammatory pathways that normally provide some protection against malignant transformation.
TNF-alpha inhibitors may impair T-cell-mediated anti-tumour immunity, theoretically increasing melanoma risk.
However, data on melanoma risk remain limited and controversial.
Biologic therapies are still safer than PUVA therapy for long-term psoriasis management
The skin cancer risk from biologic therapy is lower than that of PUVA and can be mitigated through regular surveillance.
Methotrexate, Ciclosporin, and Immunosuppression-Related Skin Cancer Risk
Methotrexate and ciclosporin are systemic immunosuppressive medications used for severe, refractory psoriasis.
Methotrexate and Skin Cancer Risk:
Increases non-melanoma skin cancer risk by 3 to 4 fold in long-term users.
The mechanism involves impaired immune surveillance of precancerous and cancerous cells
Patients on methotrexate for psoriasis require careful monitoring, including liver function tests and complete blood counts.
Skin cancer surveillance is equally critical to other monitoring.
Risk increases with cumulative dose and duration of therapy exceeding 5 years.
Requires regular dermatologic assessment every 6 to 12 months.
Ciclosporin and Skin Cancer Risk:
Carries an even higher non-melanoma skin cancer risk of up to 6 to 7 fold in long-term users.
Risk is particularly elevated when total cumulative doses exceed 100 grams.
Ciclosporin directly impairs T-cell-mediated immunity against malignant transformation.
Shorter interval between initiation and cancer diagnosis compared to other immunosuppressants.
Requires vigilant skin cancer surveillance.
Who Is at Highest Risk? Identifying High-Risk Psoriasis Patients
Certain psoriasis patients face substantially elevated skin cancer risk and require intensified surveillance.
High-Risk Patient Categories:
Patients receiving prolonged PUVA therapy, particularly those who began treatment before modern cumulative dose guidelines were established.
Patients on methotrexate or ciclosporin for more than 5 years with cumulative doses exceeding recommended limits.
Elderly psoriasis patients aged 60 and above receiving any immunosuppressive therapy, as they have reduced immune capacity.
Patients with fair skin, light eyes, and poor tanning ability have characteristics increasing baseline skin cancer risk.
Patients with a personal or family history of skin cancer indicate a genetic predisposition.
Patients with extensive psoriasis covering more than 30 percent of the body surface area, as they have more skin at risk.
Patients with concurrent sun exposure, either occupational or recreational, particularly those living in tropical regions like India, with a high UV index.
Monitoring and Surveillance Schedule for Psoriasis Patients
Surveillance Frequency by Treatment Type:
For Patients Receiving PUVA Therapy:
Baseline full-body skin examination before starting PUVA.
Complete skin examination every 6 months during active PUVA therapy.
Complete skin examination every 12 months after PUVA completion.
Lifetime follow-up is recommended even decades after PUVA completion.
For Patients on Methotrexate or Ciclosporin:
Complete skin examination every 6 to 12 months, depending on cumulative dose and duration.
More frequent screening for patients with cumulative doses exceeding recommended limits.
An annual examination is a minimum requirement for all long-term users.
For Patients on Biologic Therapy:
A complete skin examination every 12 months is recommended.
May increase to every 6 months if additional risk factors are present.
For All Patients:
Self-examination should occur monthly using the ABCDE rule.
Complete skin surveillance involves examining all body surfaces, including often-overlooked areas.
Examine scalp, ears, genitals, soles of feet, and areas beneath hair.
Dermoscopy examination may enhance the detection of early melanomas and other skin cancers.
Photography of suspicious lesions allows comparison over time for lesions with uncertain diagnosis.
How to Tell Psoriasis Plaques from Early Skin Cancer: Visual Guide

According to Dr Priya Chaturvedi, Senior Oncologist and Head of Cutaneous Oncology Unit, Tata Memorial Centre, Mumbai, the intersection of psoriasis treatment and skin cancer is one of the most underappreciated challenges in Indian oncology. As someone who manages treatment-related skin cancers in immunosuppressed patients, I can attest that the burden is substantial and growing.
Distinguishing psoriasis plaques from early skin cancer is critical for timely diagnosis.
Typical Psoriasis Plaque Characteristics:
Well-demarcated, symmetrical, elevated erythematous (red) patches with silvery-white scale.
Clear-cut borders that are distinct from surrounding normal skin.
Appear on characteristic locations: elbows, knees, scalp, and lower back.
Stable for months to years, remaining similar in size.
Itch or burn, but do not bleed unless scratched.
Usually multiple and symmetric bilaterally.
Early Skin Cancer Warning Signs:
Lesions with asymmetrical borders or irregular outlines.
Colour variation within a single lesion.
Lesions larger than 6 millimetres in diameter that are new or growing.
Lesions that bleed, ooze, or crust without being scratched.
Single, solitary lesions that stand out from the surrounding psoriasis.
Lesions with raised, rolled borders or central ulceration or depression.
Any lesion that changes in appearance, grows, or develops new symptoms.
ABCDE Rule for Identifying Concerning Lesions:
Asymmetry: One half does not match the other.
Border irregularity: Irregular, jagged, or scalloped edges.
Colour variation: Multiple colours within one lesion.
Diameter: Larger than 6 millimetres.
Evolving/changing: Growing, changing colour, or changing symptoms.
What Psoriasis Patients Should Tell Their Dermatologist
Effective skin cancer surveillance requires transparent communication between patients and dermatologists.
Critical Information to Disclose:
Inform the dermatologist of all psoriasis treatments ever received, including the number and duration of PUVA sessions.
Be specific about cumulative PUVA exposure, as dermatologists may not have access to treatment records from other institutions.
Report all current medications, including methotrexate, ciclosporin, biologic therapies, and any topical treatments.
Discuss the personal history of skin cancer or precancerous lesions.
Mention family history of skin cancer or melanoma.
Report sun exposure patterns, including occupational sun exposure, outdoor hobbies, and sun protection habits.
Discuss any new skin lesions, changes in existing lesions, or concerning symptoms like bleeding, oozing, or itching.
FAQs
Q1. Can psoriasis turn into cancer?
No, psoriasis itself does not turn into or cause cancer. Psoriasis is a chronic inflammatory skin condition driven by immune dysfunction. However, certain treatments used for psoriasis, particularly PUVA therapy, methotrexate, ciclosporin, and biologic medications, do increase skin cancer risk through immunosuppression and other mechanisms.
Q2. Should I avoid PUVA therapy?
Not necessarily, but PUVA therapy should be used cautiously and with a clear understanding of risks. PUVA remains an effective treatment for generalised psoriasis, particularly when other treatments are unavailable or ineffective.
Q3. What cancer can cause itchy skin?
While skin cancer itself can cause itching, most skin cancers are relatively asymptomatic. However, any new itchy skin lesion, especially if it persists longer than 3 weeks or shows features concerning for cancer, warrants immediate dermatologic evaluation.
Q4. Should I stop taking my psoriasis medication due to the fear of skin cancer?
Do not stop psoriasis medications without consulting your dermatologist. Untreated psoriasis can severely impact quality of life and cause other health complications. Instead, discuss with your dermatologist whether safer treatment options are available for your specific situation.
Final Thoughts
The relationship between psoriasis, its treatments, and skin cancer risk is complex and often misunderstood by patients and healthcare providers alike. While psoriasis itself does not cause cancer, certain psoriasis treatments significantly increase the risk and require careful consideration, patient selection, and rigorous surveillance.
For the 2.8 million Indians living with psoriasis, understanding this relationship is essential for making informed treatment decisions. If you have psoriasis and are considering or currently receiving treatment, discuss skin cancer risk openly with your dermatologist.
Implement regular self-surveillance, adhere to recommended clinical examination schedules, and promptly report any concerning skin changes. With appropriate vigilance and early detection, skin cancer in patients with psoriasis is highly treatable and often curable.
.png "mrmed")
Read Also
References
British Journal of Dermatology. PUVA therapy cumulative dose and squamous cell carcinoma risk — long-term follow-up study [Internet]. UK: BJD; 2019 [cited 2026 May 27].https://onlinelibrary.wiley.com/journal/13652133
JAMA Dermatology. Psoriasis, immunosuppressive therapy, and risk of non-melanoma skin cancer — large cohort study [Internet]. USA: JAMA Dermatology; 2016 [cited 2026 May 27].https://jamanetwork.com/journals/jamadermatology
British Association of Dermatologists. PUVA therapy guidelines and skin cancer surveillance recommendations [Internet]. UK: BAD; 2024 [cited 2026 May 27].https://www.bad.org.uk/
Disclaimer: This article is for general informational purposes only and is not a substitute for professional medical advice. If you have psoriasis and are concerned about skin cancer risk, consult a qualified dermatologist for a personalised assessment and recommendations. Treatment decisions should be based on individual risk-benefit analysis conducted with your healthcare provider. Early detection of skin cancer significantly improves prognosis and outcomes.















Comments